Crossing State Lines: Why Your Move Might Mean Losing Access to Healthcare and Insurance

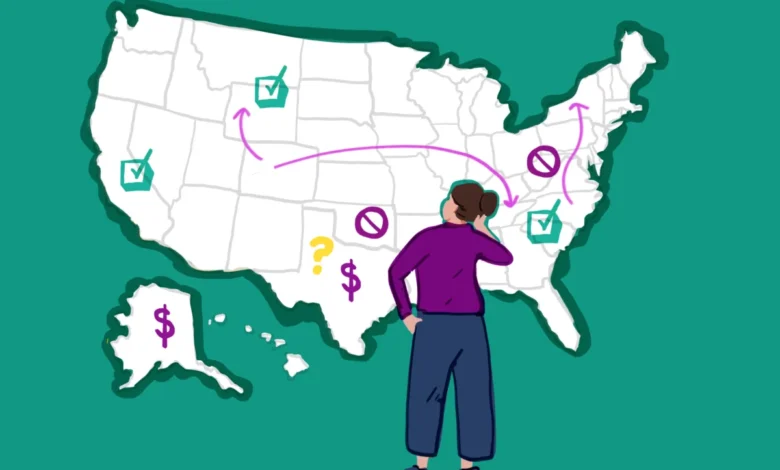
When young adults pack up their belongings to cross state lines for a new job, higher education, or a change of scenery, they typically budget for moving trucks, security deposits, and the logistics of setting up a new household. However, healthcare logistics—such as finding a new primary care physician, transferring prescriptions, and navigating an entirely unfamiliar health insurance market—frequently get left off the pre-move checklist.
This oversight is becoming increasingly hazardous as state-by-state discrepancies in health policy, insurance regulations, and reproductive and medical rights widen. For recent graduates and young professionals, a cross-country move is no longer just a geographical shift; it is a fundamental alteration of their healthcare safety net.
The Realities of Interstate Relocation
Consider the experience of Jael Samano, who recently relocated from Illinois to Wisconsin following her college graduation. The move brought expected milestones: a new career as an environmental consultant and the milestone of living entirely on her own. Yet, it was only during a final pre-move session with her therapist that Samano confronted the reality of her impending administrative hurdles. She would need to sever ties with her established healthcare providers, hunt for new practitioners in an unfamiliar market, and decipher a completely different employer-sponsored health insurance plan.
Reflecting on the experience, Samano noted that securing healthcare access has rapidly climbed to the top of her priorities, describing the realization as an "adult-y" necessity that she initially underestimated.
Samano’s situation is far from unique. Millions of Americans relocate annually, and many assume their healthcare coverage and rights easily cross state borders. In reality, health insurance networks, state Medicaid policies, telehealth regulations, and clinical
care laws shift dramatically at every state border. Experts emphasize that failing to research these changes beforehand can leave individuals facing unexpected coverage gaps, high out-of-pocket costs, or sudden legal restrictions on specific medical treatments.
Navigating Insurance Options: The ACA and the Medicaid Maze
For those who do not secure health insurance through an employer or university, navigating the transition requires careful timing and an understanding of federal versus state regulations.
Moving is officially classified as a "qualifying life event" under the Affordable Care Act (ACA). This designation allows individuals to enroll in a new ACA health insurance plan through HealthCare.gov outside of the standard autumn open enrollment window. However, finding an affordable plan that includes preferred local doctors and hospitals within its network can be a complex endeavor.
The landscape grows even more complicated when examining Medicaid, the joint federal and state program that provides free or low-cost health coverage to millions of low-income individuals, people with disabilities, and families. While federal guidelines establish baseline requirements, individual states hold significant autonomy over how their Medicaid programs are structured and who qualifies.
As of recent data, 40 states and Washington, D.C., have expanded Medicaid under the ACA, raising income eligibility thresholds to allow single adults earning up to roughly $22,000 annually to qualify. Yet, non-expansion states—including populous regions like Texas, Florida, and Tennessee—have maintained stringent restrictions. In these states, single adults without children face extraordinarily high hurdles to qualify for coverage, regardless of financial need.
Jennifer Tolbert, deputy director of the Program on Medicaid and the Uninsured at KFF, a health policy research organization, highlights the gravity of this disparity. "Medicaid can be an important source of coverage for people in transition," Tolbert said. "If you need Medicaid as a source of coverage, you should not move to states that have not adopted the Affordable Care Act’s Medicaid expansion."
Compounding these challenges are upcoming federal policy shifts. Federal work requirements for Medicaid are scheduled to take effect in the majority of states by 2027. This regulatory change will introduce mandatory reporting procedures and additional paperwork for beneficiaries, increasing the risk of administrative churn and accidental coverage losses for young workers moving between states.
The 26-Year-Old Rule and Parental Plan Limitations
Many young adults rely on the ACA provision allowing them to remain on their parents’ employer-sponsored health insurance plans until the end of the calendar year in which they turn 26. For those moving out of state, this can serve as a vital safety net, ensuring continuous coverage without the immediate stress of purchasing an individual policy.
However, retaining coverage under a parent’s plan while living in a different state comes with distinct limitations. Most notably, health insurance provider networks are often geographically restricted. A preferred provider organization (PPO) plan may offer out-of-state coverage, but often with higher deductibles and coinsurance rates. Meanwhile, health maintenance organization (HMO) plans frequently provide zero coverage outside of emergency care when the policyholder resides outside the home network’s designated service area.
Furthermore, a small number of states have enacted legislation expanding parental coverage eligibility beyond the federal age limit of 26. For example, Florida law permits young adults to stay on a parent’s health plan until age 30, provided they meet specific criteria, such as maintaining state residency or full-time student status. Several other jurisdictions offer extended coverage past age 26 specifically for adult children with documented disabilities. Young adults must verify these nuances with both their parents’ insurance provider and the HR department sponsoring the plan before finalizing a move.
Divergent State Laws and Healthcare Access
Beyond insurance mechanics, the legal parameters governing what medical care is accessible vary starkly across the United States. These policy divergences directly impact everything from chronic pain management to reproductive health and emergency care.
Consider the landscape of medical and recreational cannabis. Approximately 40 states permit residents to purchase medicinal cannabis with a doctor’s recommendation, and roughly two dozen states have legalized recreational use. Most other jurisdictions permit the use of low-THC CBD products, but states like Idaho and Kansas maintain total prohibitions on cannabis in all its forms, according to data from the National Conference of State Legislatures. A patient relying on medical cannabis to manage chronic conditions in one state could face criminal penalties or a total loss of access upon crossing into a prohibition state.
Reproductive healthcare and maternal medicine present even more pronounced regulatory divides. Following the dismantling of federal constitutional protections for abortion, 13 states have enacted total bans on the procedure, while at least six others have implemented strict gestational limits within the first trimester.
Public health experts and legal analysts point out that the implications of these bans extend far beyond elective abortion care. Restrictive legislation and vague statutory language have generated widespread confusion among clinicians, occasionally delaying or complicating emergency medical care for patients experiencing complex miscarriages or ectopic pregnancies—situations documented in investigative reports across states with severe abortion restrictions.
Alina Salganicoff, director of the Women’s Health Policy Program at KFF, stresses the importance of proactive research. "If you’re moving to a new state and you’re considering making this kind of change, it’s important to research and know what your options are before you get there, not once you get there and you can’t make changes," Salganicoff warned.
Telehealth, Licensing, and the Continuity of Care
For individuals managing mental health conditions or ongoing medical treatments, maintaining a relationship with an existing provider via telehealth can seem like a seamless solution to an interstate move. However, regulatory frameworks governing telemedicine do not recognize state borders automatically.
Historically, medical and mental health licenses are issued at the state level. This means a physician, therapist, or clinical specialist must hold a valid license in the specific state where the patient is physically located at the time of the appointment.
While the COVID-19 pandemic catalyzed temporary emergency flexibilities that eased interstate telehealth, many of those provisions have expired or been modified. Today, licensure requirements vary widely depending on the profession and the states involved. Some healthcare fields utilize interstate compacts—such as the Psychology Interjurisdictional Compact (PSYPACT) or the Interstate Medical Licensure Compact—which streamline the process for licensed professionals to practice in multiple participating states.
Nevertheless, health policy experts advise patients to consult directly with their current providers before packing their bags. Confirming whether a therapist or physician is legally authorized to provide remote care across state lines can prevent abrupt interruptions in treatment regimens that require long-term stability.
Preparing for the Administrative Transition
As workforce mobility remains high and young professionals continue to relocate for economic opportunities, healthcare literacy during major life transitions is increasingly viewed as a vital life skill. Public health advocates recommend that anyone planning an interstate move take a series of deliberate steps well in advance:
- Audit Current Coverage: Determine whether existing insurance policies—whether employer-sponsored, ACA marketplace, or a parent’s plan—offer adequate out-of-state provider networks or emergency coverage.
- Review State-Specific Policies: Research the new state’s Medicaid expansion status, reproductive health laws, and regulations concerning specialized treatments or prescriptions.
- Verify Telehealth Status: Check if current mental and physical health providers can legally continue care remotely under state licensure laws or multi-state compacts.
- Establish Care Early: Identify in-network primary care physicians and specialists in the destination city prior to arrival to avoid delayed prescription refills or gaps in chronic disease management.
By treating healthcare access with the same logistical rigor as housing and employment, movers can mitigate the administrative shocks of crossing state lines and protect their physical and financial well-being.