Navigating the 2027 ACA Open Enrollment: Premium Shifts, New Identity Checks, and Broker Restrictions

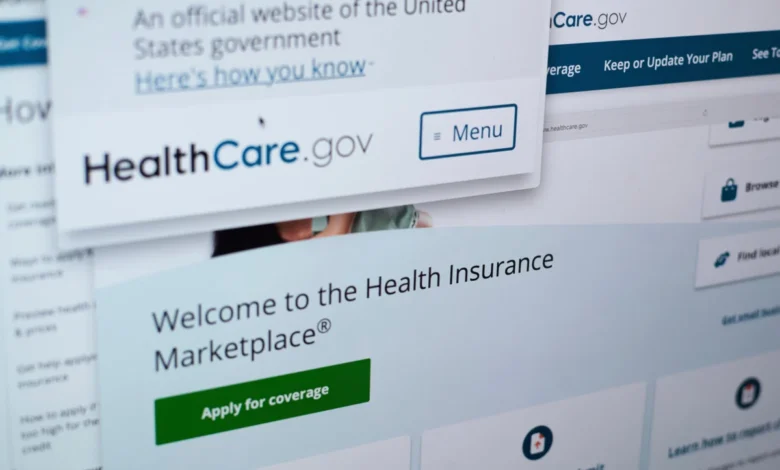
As the open enrollment period for Affordable Care Act (ACA) health insurance coverage for 2027 approaches, consumers across the United States are preparing to navigate a complex landscape defined by shifting federal regulations, ongoing cost adjustments, and tighter administrative controls. Set to officially launch on November 1 in the majority of states—though some state-run exchanges have established alternative calendars or already opened systems for early window shopping—the upcoming enrollment window introduces significant modifications designed to curb fraudulent activity while simultaneously altering the operational dynamics for brokers and policyholders alike.
These adjustments arrive on the heels of a turbulent period for the federal marketplace. Following the expiration of enhanced subsidies at the end of 2025, overall enrollment numbers have experienced a downward trajectory. Policy experts note that the removal of these enhanced financial supports led millions of Americans to either drop or lose their coverage during the initial months of the year. Conversely, the Trump administration has framed the falling enrollment figures as a policy victory, directly attributing the reduction to aggressive initiatives aimed at eliminating marketplace fraud. Among these efforts was an administrative cancellation in August of policies covering approximately 760,000 enrollees whose accounts were flagged for improper or suspicious sign-ups, though a minor fraction of those individuals have since successfully navigated the reinstatement process.
Enhanced Identity Verification and Consumer Safeguards
One of the most consequential changes facing shoppers this year is the implementation of heightened scrutiny protocols targeting both consumers and insurance agents. Designed specifically to thwart unauthorized enrollments and fraudulent brokerage practices, these new rules threaten to introduce friction and potential delays into the application process.
According to guidelines issued by the Centers for Medicare & Medicaid Services (CMS), these revised verification standards apply strictly to consumers utilizing agents or brokers to enroll through the federal marketplace, which currently services 29 states. State-based exchanges, which operate under independent regulatory frameworks, are largely exempt; historically, many of these state-run platforms have reported higher success rates in proactively preventing fraudulent sign-ups without requiring sweeping federal overhauls.
Under the updated federal mandates, every consumer working with an agent in the marketplace must secure a unique, one-time confirmation code or authorization link before an agent can officially enroll them or modify an existing policy. This security token is delivered via SMS text message, electronic mail, or an automated voice call originating directly from the private enrollment platforms utilized by the broker. For returning consumers, this requirement introduces a potential logistical hurdle: individuals with outdated or incorrect contact information must first contact the federal marketplace directly or log into their online profiles to update their data before authorization can proceed.
Furthermore, the federal framework designates certain demographics as "high-risk," subjecting them to mandatory identity proofing before they are permitted to authorize an agent. CMS defines high-risk participants as first-time applicants, existing policyholders whose applications involve an interstate relocation, individuals partnering with a newly assigned or unfamiliar broker, and consumers selecting plans with a monthly premium of $30 or less.
Insurance professionals have offered mixed evaluations of these specific risk parameters. Joshua Brooker, an agency director based in Pennsylvania, suggests that federal regulators targeted interstate moves and broker changes because those scenarios frequently characterize bad-faith attempts by rogue actors to impersonate legitimate consumers. Regarding the $30 monthly threshold, Brooker notes that zero-premium or ultra-low-cost plans are prime targets for malicious agents seeking unauthorized commissions. In some instances, bad actors have personally covered the nominal monthly premiums while reaping substantial commission profits from the underlying carrier, leaving the unsuspecting consumer completely unaware of the policy change.
Despite the logical underpinnings of these safeguards, industry experts have expressed apprehension regarding their practical execution. Brooker estimates that as many as one in five consumers may be flagged for additional identity verification, a barrier that could cause frustrated applicants to abandon the enrollment process entirely.
Consumers categorized as high-risk must verify their identities through CMS-approved third-party credit bureaus, such as Experian, which typically generate authentication queries based on credit history. Individuals who fail this automated verification are directed to contact customer support desks or complete their applications independently via Healthcare.gov, a process that necessitates uploading official identification documents such as a passport, state-issued driver’s license, or immigration paperwork.
Stacey Pogue, a senior research fellow at the Center on Health Insurance Reforms at Georgetown University, acknowledges the dual nature of these policy adjustments. While the measures represent a targeted response to systemic fraud, Pogue cautions that they risk introducing formidable obstacles for vulnerable populations. She notes that legitimate individuals may encounter difficulties not due to fraud, but rather because they lack established credit files, have recently relocated, or have experienced legal name changes.
Broker Restrictions and Legal Challenges
In tandem with heightened identity checks, regulatory measures concerning insurance intermediaries are reshaping the marketplace infrastructure. In September, CMS instituted a formal moratorium prohibiting brokers new to the ACA ecosystem from offering marketplace coverage for the upcoming plan year. Specifically, agents who were not officially registered with the federal marketplace during the previous calendar year are barred from assisting with 2027 enrollments until February at the earliest—well past the conclusion of the open enrollment window.
Federal regulators justified the moratorium by pointing to compliance data from the previous year, which indicated that a disproportionate share of administrative complaints and compliance failures originated from newly registered agents and brokers. Consequently, regulatory bodies have systematically removed hundreds of non-compliant intermediaries from the marketplace network throughout the year.
While established brokerage leaders acknowledge the underlying necessity of reining in bad actors, they warn of severe short-term consequences for the broader insurance market. Jason Fine, director of a Florida-based brokerage, has frequently reported instances of unauthorized policy switching by rogue agents to federal authorities. While supporting long-term regulatory cleanup, Fine argues that the sudden enforcement timeline fails to account for operational chaos.
For many independent agencies, staffing models rely on scaling down core teams post-enrollment and aggressively hiring toward the end of the year. Fine had intended to expand his modest five-person staff with up to 10 additional agents, but industry recruiters confirmed that finding pre-registered, available talent under the new moratorium is virtually impossible. Industry analysts suggest that this restriction inadvertently advantages large-scale call centers—entities frequently scrutinized for aggressive marketing tactics—because their permanent, year-round staffing structures allow them to absorb regulatory shocks more effectively than smaller, community-based agencies.
This friction has erupted into formal legal action. On October 15, the National Association of Benefits and Insurance Professionals filed a federal lawsuit against the administration, arguing that the broker moratorium unfairly penalizes approximately 19,000 qualified professionals seeking to legally market ACA plans. This was followed by a separate legal filing on October 21 by Health Agents for America, which requested an emergency temporary restraining order against the directive. Ronnell Nolan, president of the organization, emphasized that the blanket restriction harms legitimate businesses that have heavily invested in training new personnel who are now legally barred from practicing.
Given these workforce constraints, policy experts advise consumers to act decisively. Georgetown’s Pogue stresses that individuals relying on professional guidance should schedule appointments early, as a diminished pool of active brokers will likely experience heavily compressed scheduling capacities.
Persistent Affordability Pressures and Financial Metrics
Beyond administrative hurdles, affordability remains the central challenge for consumers evaluating their healthcare options. Following the expiration of enhanced federal subsidies enacted by Congress, most marketplace participants experienced immediate financial shocks through reduced assistance and higher out-of-pocket costs, compounded by double-digit premium increases across multiple states.
For the upcoming 2027 coverage year, the fundamental structure of subsidies remains intact, scaling in accordance with household income and benchmark plan pricing—specifically, the second-lowest-cost silver tier available in a given geographic region. However, because enhanced subsidies have expired, overall financial support remains less robust than in prior years.
Louise Norris, a health policy analyst with HealthInsurance.org, notes that while overall affordability will remain relatively stable for those who managed the transition through the previous year, underlying cost drivers continue to exert upward pressure on rates. Last year’s average premium increases hovered near 26%, marking one of the steepest hikes in the history of the marketplace. Insurers largely attributed those adjustments to actuarial concerns regarding healthier enrollees dropping coverage in the wake of subsidy rollbacks, alongside macroeconomic pressures including general inflation, persistent labor shortages, and rising underlying medical care costs.
For the 2027 benefit year, projected premium increases are showing slight moderation, averaging in the mid-double digits. Nevertheless, consumer advocates warn that structural limits on financial assistance continue to pose a threat to long-term coverage retention. Subsidies remain strictly tied to federal poverty guidelines, phasing out entirely for households earning more than 400% of the federal poverty level. During the current open enrollment cycle, this income cutoff translates to $63,840 for a single individual, $86,560 for a two-person household, and $109,280 for a family of three.
Anne Petry, co-owner of Jaggi Petry Insurance & Investments in Forsyth, Illinois, identifies affordability as the single most critical variable facing enrollees. She cautions that cumulative financial pressures are rapidly approaching a breaking point for working-class families.
To mitigate these expenses, insurance specialists strongly advise enrollees to avoid automatic policy renewals. Because carrier networks, pricing models, and available plan offerings shift annually—with major insurers like Cigna scaling back their operational footprints in specific regional markets—consumers who fail to actively compare options risk missing out on more cost-effective alternatives. Analysts recommend evaluating comprehensive plan structures, including deductibles and total cost-sharing provisions, rather than focusing exclusively on monthly premiums.
Compounding these calculations are increases in statutory out-of-pocket maximum limits. The maximum allowable threshold for consumer spending on deductibles, copayments, and coinsurance within in-network parameters is scheduled to rise by approximately 13% for 2027. Individual out-of-pocket maximums will climb to $12,000, while family plans will reach $24,000, up from $10,600 and $21,200, respectively, during the prior year. Reduced caps continue to apply exclusively to low-income households earning up to 2.5 times the federal poverty level.
Immigration Status and Subsidy Eligibility Changes
Compounding the regulatory overhaul are new statutory exclusions stemming from legislative changes passed by Congress, most notably the One Big Beautiful Bill Act. These provisions significantly narrow the scope of individuals eligible for federal financial assistance by stripping ACA subsidy eligibility from various categories of lawfully present immigrants.
Under the revised criteria, holders of temporary H-1B work visas, refugees, asylees, individuals possessing temporary protected status, and applicants with pending green-card petitions are no longer eligible for marketplace subsidies. Lawful access to subsidized coverage is now restricted primarily to three specific demographic groups: permanent legal residents (green-card holders), designated Cuban and Haitian nationals, and citizens of Pacific Island jurisdictions including Micronesia, the Marshall Islands, and Palau.
As the November 1 open enrollment kickoff approaches, policy analysts, consumer advocates, and insurance intermediaries alike emphasize that proactive planning is essential. With compressed broker availability, stringent identity verification protocols, and evolving financial thresholds, consumers are urged to review their coverage options early to secure optimal healthcare protection for the coming year.